Suicide Prevention
September 9, 2026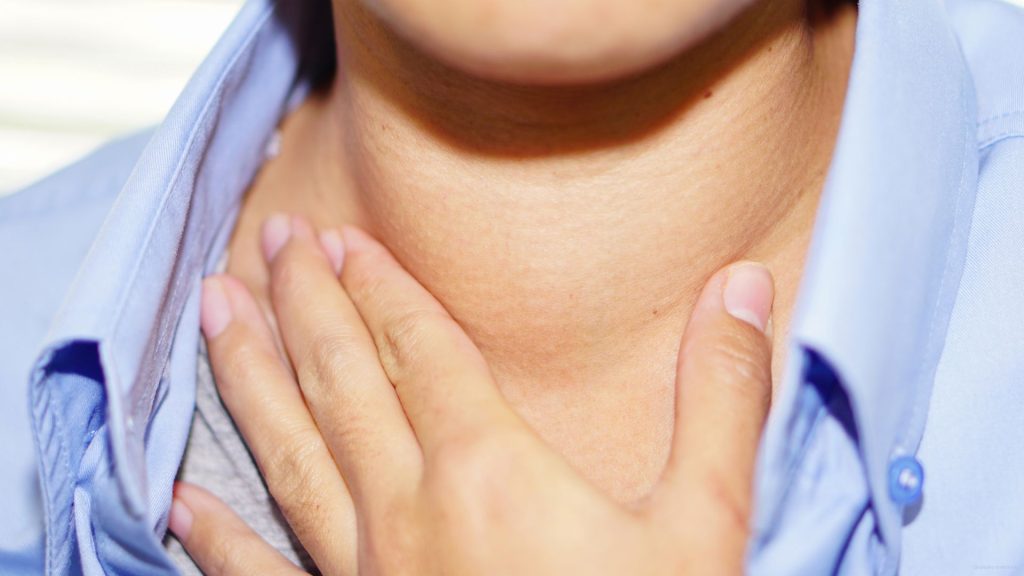
TRENDING MEDICAL EDUCATION TOPIC: Thyroid Cancer
What is the problem?
The American Cancer Society estimates 45,240 new cases of thyroid cancer and 2,320 deaths in the United States in 2026, at an average age at diagnosis of 51. Survival is excellent for most patients, which means the disease is managed less as an acute cancer than as a decades-long course that passes through several hands.
In August 2025, the American Thyroid Association issued its first full revision of the adult guidelines since 2015. The recurrence risk model moved from three tiers to four. More patients are now managed with lobectomy or active surveillance rather than total thyroidectomy and radioactive iodine. Molecular diagnostics carry greater weight in risk assignment, and surveillance is formally de-escalated for low-risk patients with an excellent response.
No single specialty sees the whole pathway. Surgeons decide extent of resection, pathologists and molecular testing shape risk assignment, nuclear medicine physicians determine adjuvant therapy, endocrinologists set surveillance intensity, and primary care physicians carry follow-up for the next several decades. A risk category assigned in one setting drives decisions in the next, and it often arrives incomplete or gets read against the older three-tier system. The result is overtreatment of indolent disease in some patients and uneven follow-up in the ones at genuine risk.
This activity reviews what the 2025 recommendations mean at each stage of care and what each specialty needs to communicate at the handoffs between them.
Proposed Learning Objectives
At the conclusion of this activity, the learners will be able to:
- Integrate thyroid imaging, cytopathology, molecular diagnostics, and patient characteristics to determine initial management strategy, including candidacy for active surveillance, lobectomy, or total thyroidectomy
- Apply the 2025 ATA four-tier recurrence risk classification to assign postoperative risk and identify where it differs from the prior three-tier system
- Weigh the anticipated risks and benefits of adjuvant radioactive iodine across the four risk categories, with attention to the low-intermediate and intermediate-high groups where the decision is least settled
- Apply dynamic risk stratification to revise risk over time and adjust surveillance intensity accordingly, including de-escalation for low-risk patients with an excellent response
- Identify the handoff points between surgery, pathology, nuclear medicine, endocrinology, and primary care where risk information is most often lost, and describe what each specialty needs to receive at each point
If your medical staff needs an update on thyroid cancer, consider contacting our office to book a speaker at 714-505-4777 or info@speakersnetwork.com.

info@speakersnetwork.com
REFERENCES
https://www.cancer.org/cancer/types/thyroid-cancer/about/key-statistics.html
https://pubs.rsna.org/doi/full/10.1148/rg.240021
https://acsjournals.onlinelibrary.wiley.com/doi/full/10.3322/caac.70043